A preventable disease, an official defeat, and a question about algorithms#
On 17 November, the Pan American Health Organization (PAHO) announced that endemic measles transmission had been re-established in Bolivia, Mexico and the United States, and that all three countries had lost their measles elimination status (PAHO). The same week, the US Centers for Disease Control and Prevention (CDC) reported 5,412 confirmed US cases for 2026 as of 12 November (CDC). Measles has a safe, effective vaccine and a well-understood route of spread. If any viral disease is preventable, this is it.
So where does artificial intelligence come in? The honest answer is "in a smaller role than the headlines about AI in medicine suggest, but a useful one". Researchers have been building machine learning models for measles for years, and a steady trickle of 2026 papers claims they can map risk, flag districts and sharpen surveillance. Whether those tools would have spared anyone this autumn's news is a different matter.
This post separates what the evidence supports from what it does not. It is built around the PAHO decision and the latest CDC figures, then looks at the peer-reviewed literature on forecasting, risk prediction and surveillance. The short version: AI is good at some narrow jobs, a classic statistical model is still hard to beat at others, and no forecasting tool can replace the 95 per cent vaccine coverage that PAHO says is the route back.
Background: what "elimination" means and what a forecasting model does#
Elimination does not mean zero measles. It means the disease is no longer spreading continuously inside a country. PAHO's Regional Monitoring and Re-Verification Commission applies a clear test: if the same genotype and lineage of the virus circulates for more than 12 months, transmission is considered re-established (PAHO). For the United States the outbreak began on 20 January 2025 and passed that 12-month threshold on 20 January 2026, while Mexico's began on 1 February 2025 (PAHO).
Measles is unforgiving because it is so contagious. PAHO says one infected person can pass the virus to as many as 18 susceptible people, and that it can cause pneumonia, encephalitis, blindness and death (PAHO). That arithmetic is why pockets of unvaccinated people matter so much, even when a national average looks healthy.
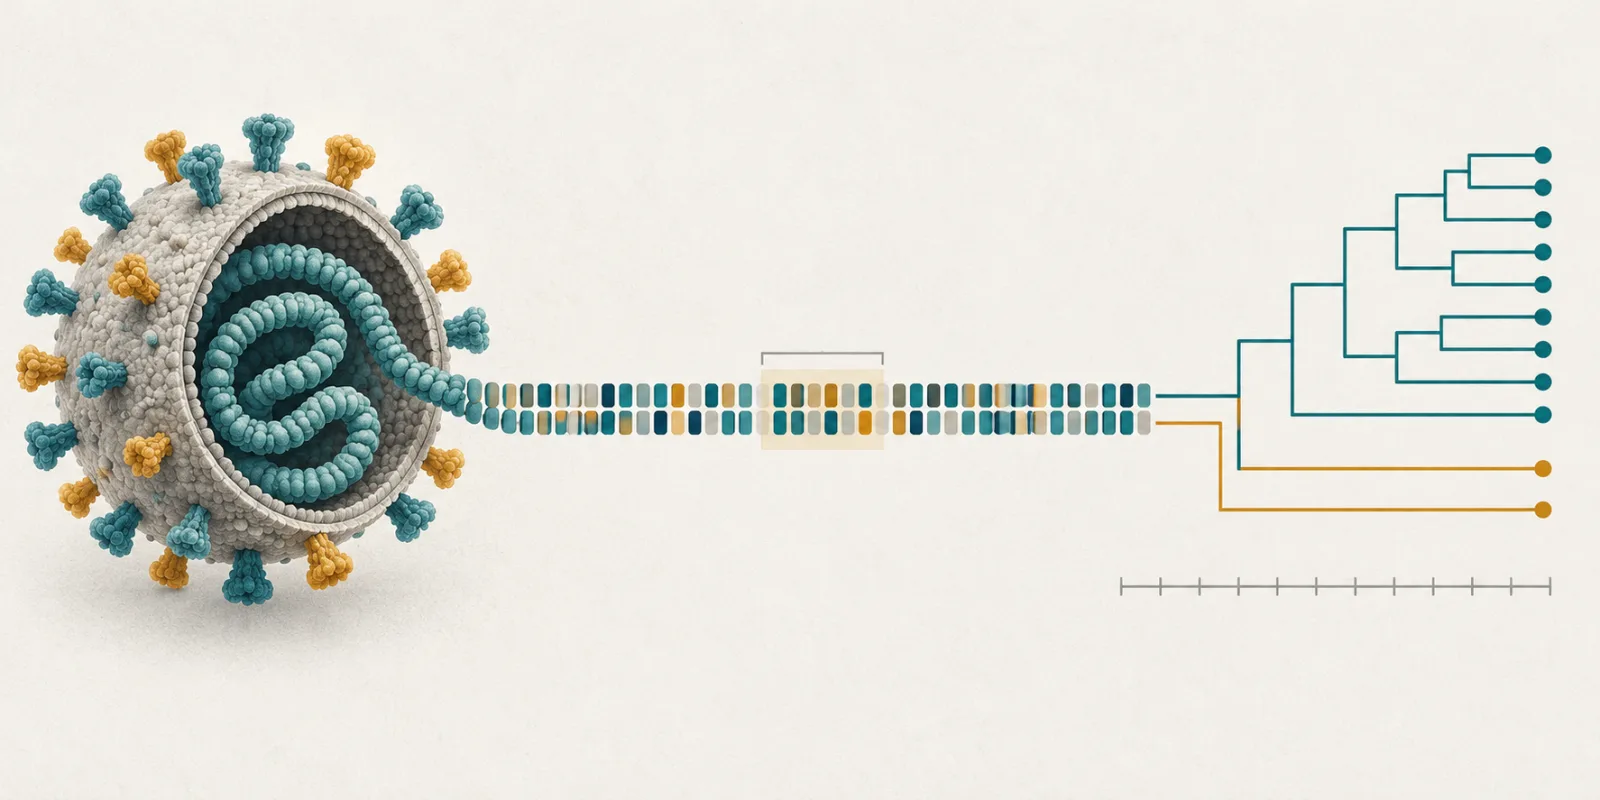
Now the AI side, with a few terms made plain. A forecasting model takes past case counts and predicts future ones. A risk model takes features of a place (say, vaccination coverage, population density, travel) and estimates how likely an outbreak is there. Machine learning means the computer finds the pattern in historical data rather than being given a formula. A mechanistic model is the older approach: it writes down how the disease spreads, with susceptible, infected and recovered people, and fits the numbers. Two scores come up repeatedly below. AUC measures how well a model ranks places from low to high risk (1.0 is perfect, 0.5 is a coin toss). Sensitivity is the share of real outbreaks the model catches, and positive predictive value is the share of its alarms that turn out to be real.
What the numbers say about the 2026 resurgence#
PAHO reported 58,213 confirmed measles cases and 82 deaths across the Americas as of 13 November 2026, against 12,806 cases in the same period of 2025 (PAHO). That is more than four times last year's count. In the United States, CDC data show 43 new outbreaks in 2026, with 96 per cent of confirmed cases outbreak-associated and 96 per cent in people who were unvaccinated or whose status was unknown (CDC).
Eleven per cent of 2026 US cases, 591 of 5,412, were hospitalised, and six deaths have been recorded (CDC). By 10 September the United States had already recorded 3,294 confirmed cases, its largest annual total since elimination was declared in 2000 (Emerging Infectious Diseases). The chart below puts these figures side by side.
The pattern matters for modelling. These are not random scatterings of cases. They are clusters inside communities with immunity gaps, and PAHO makes the point directly: national vaccination figures can mask local disparities, which leave particular communities and areas exposed (PAHO). A model that sees only a national average is blind to the problem. A model that can see counties or districts has a chance.
Where machine learning has helped, and by how much#
The strongest evidence is for risk ranking, not prophecy. A US study in JMIR Formative Research compared a machine learning method called XGBoost with plain logistic regression for predicting which counties would have measles cases (JMIR Formative Research). XGBoost scored an AUC of 0.920 to 0.926 against 0.900 to 0.908 for logistic regression (JMIR Formative Research).
That is a modest gain, and the detail is instructive. Logistic regression caught more outbreaks (sensitivity 0.837 to 0.857 against 0.704 to 0.735), but its alarms were far less reliable, with a positive predictive value of 0.122 to 0.141 against 0.340 to 0.367 for XGBoost (JMIR Formative Research). The authors note the prediction threshold can be tuned to match each county's resources and risk tolerance (JMIR Formative Research). In plain terms: you can choose between a net that catches nearly everything and carries many false alarms, or one that is pickier. That is a policy decision, not a mathematical one.
A 2026 study in BMC Infectious Diseases applied the same family of method in Bangladesh. The authors compared eight classifiers on 2017 to 2023 district data combined with climate, socio-demographic, healthcare and vaccination indicators, and selected XGBoost, which reached an AUC of 0.838 and an accuracy of 81.3 per cent (BMC Infectious Diseases). The authors describe this as supporting district prioritisation rather than precise case-level prediction (BMC Infectious Diseases). Socio-demographic factors contributed 41.37 per cent of the model's predictive weight, climatic factors 39.22 per cent and healthcare variables 19.41 per cent, and vaccination coverage showed lower standalone importance (BMC Infectious Diseases).
That last finding deserves a caution. It does not show vaccination is unimportant. It shows that in that dataset, coverage added less on top of the other variables, which the authors read as vaccination modulating risk rather than driving it alone (BMC Infectious Diseases).

Forecasting, and why older maths still earns its keep#
Forecasting the number of cases over time is a harder job than ranking places. In a PLOS Computational Biology study, a simple machine learning method called LASSO matched a widely used mechanistic model (TSIR) for short to medium-term forecasts of measles in England and Wales, and may have outperformed it for the less regular outbreaks seen in US cities between 1932 and 1945 (PLOS Computational Biology). Both approaches lost accuracy for longer-term predictions in highly irregular, post-vaccination outbreaks (PLOS Computational Biology). The LASSO model also recovered, from the data alone, the way the mechanistic model treats the depletion of susceptible people (PLOS Computational Biology).
A later study went further with neural networks. A spatial-feature neural network achieved lower forecasting error than the mechanistic model across most windows, though the mechanistic model was comparably good for short-term forecasts in large cities (PLOS Computational Biology). The same authors found that feeding the mechanistic model's estimate of the susceptible population into a physics-informed neural network improved both its forecasts and its parameter estimates (PLOS Computational Biology).
Notice the common thread. The best results come from blending the two approaches, not from replacing one with the other. Those studies used historical data from England and Wales, so they are tests of method, not forecasts of the current American outbreak.
The 2026 resurgence also exposed a weakness that no model design fully fixes. A 2026 study in Frontiers in Epidemiology trained four forecasting models on US surveillance data going back to 1997, held out the first four months of 2026, and found that every model underestimated the cases observed by 1 May (Frontiers in Epidemiology). The authors concluded that 2026 represents a distinct, more severe outbreak regime that cannot be explained as a continuation of past trends (Frontiers in Epidemiology). These four models were classical count-regression and time-series methods, not AI, so this is not a defeat for machine learning specifically. It is a reminder that any model trained on the past struggles when the world changes.
The evidence gap between research and routine use#
A narrative review in the Journal of Clinical Medicine synthesised 46 studies, 31 on measles directly and 15 on related diseases, from searches run between June and December 2025 (Journal of Clinical Medicine). Its summary table gives a usefully blunt picture, reproduced in simplified form here.
| Method | Measles task | Compared with | Reported result | Maturity |
|---|---|---|---|---|
| SEIR (compartmental) | Transmission dynamics, scenario analysis | None (baseline) | Good qualitative fit to outbreaks | Established (review) |
| ARIMA | Short-term incidence forecasting | None (baseline) | Competitive for short horizons | Established (review) |
| XGBoost | County-level outbreak risk | Logistic regression | Higher AUC (about 5 to 15 per cent) and sensitivity | Emerging (review) |
| Random forest | Case and risk classification | Regression, decision trees | Higher accuracy (about 3 to 10 per cent) | Emerging (review) |
| Convolutional neural network | Rash image diagnosis | Clinician assessment | Comparable or better in controlled datasets | Experimental (review) |
| LSTM (deep learning) | Time-series forecasting | ARIMA | Context-dependent; gains in long, non-linear series | Experimental (review) |
| Hybrid mechanistic and deep learning | Scenario modelling, adaptive forecasting | SEIR | Better fit under changing dynamics | Experimental (review) |
The review's headline finding is sobering. Across all 46 studies, the authors found no peer-reviewed evidence that any AI or hybrid model had been integrated into routine national measles surveillance or formally adopted for vaccination policy decisions (Journal of Clinical Medicine). The image-classification accuracies of up to 99 per cent came from limited, curated datasets with no prospective validation in clinics or the field (Journal of Clinical Medicine). No study had validated its model on data from a different country or region (Journal of Clinical Medicine).
The authors also flag two structural problems. Measles data are mostly long stretches of zero interrupted by sudden spikes, which makes the classes badly imbalanced (one cited study had a class ratio of 1,696 to 78) (Journal of Clinical Medicine). And publication bias likely inflates the reported performance of AI methods, because negative results are less often published (Journal of Clinical Medicine). Nothing in this post can fix those limits. It is worth keeping them in mind whenever a new paper promises an accuracy figure.
Surveillance, genomes and the unglamorous work AI could support#
The PAHO ruling hinged on one question: did the same virus lineage keep circulating? That is a genomic and epidemiological question, and it is where data tools matter most. The Journal of Clinical Medicine review notes that genomic surveillance of measles genotypes is already operational in many reference laboratories and could improve outbreak attribution, and suggests federated learning (training a shared model across countries without exchanging raw patient data) as a way to support cross-border elimination verification (Journal of Clinical Medicine). Both are proposals, not deployed systems.
Data plumbing is a quieter contribution. A 2025 paper in JAMIA Open describes Measles Tracker, a near-real-time data hub that harmonises US surveillance data from official reports, epidemiological bulletins and news-captured outbreak reports (JAMIA Open). Its authors present it as a complementary tool to official public health systems, not a replacement, and it does not interfere with contact tracing or vaccination work (JAMIA Open). That is probably the right humility for most surveillance technology.
Where AI has a larger claim is in designing vaccines for diseases that have no good one yet. A 2026 review in Frontiers in Pharmacology describes machine learning being applied across antigen discovery, epitope prediction, structural optimisation, immunogenicity assessment and safety evaluation (Frontiers in Pharmacology). Its authors also warn about data bias, limited representation of populations from low- and middle-income countries, and the need for interpretable models that regulators can scrutinise (Frontiers in Pharmacology). Measles does not need a new vaccine. It needs the existing one delivered to everyone, which is a logistics and trust problem, not a molecular one.
What the evidence supports, and what to do with it#
Three conclusions follow, and they are my reading of the evidence, not a consensus statement. First, risk-ranking models can plausibly help health departments decide where to send vaccination teams and outreach, particularly where local data are good. The sensitivity and false-alarm trade-off in the county study is the kind of choice a public health team can tune to its own resources (JMIR Formative Research).
Second, forecasts of the total number of cases should be treated with care. The 2026 resurgence outran models fitted on a quarter-century of history (Frontiers in Epidemiology). Planning around a forecast that assumes the future looks like the past is a risk in its own right.
Third, the route back is not computational. For the United States to regain elimination status it must submit a corrective action plan and then show it has been free of the virus for 12 months, according to Reuters reporting of PAHO officials' remarks (Reuters). PAHO's own path is at least 95 per cent coverage with both vaccine doses in every community, supported by strong surveillance and effective outbreak response (PAHO). The Americas has done this before: it regained regional elimination status in 2024 after Venezuela and Brazil interrupted their transmission (PAHO).
For researchers, the open problems are concrete: prospective validation inside real surveillance systems, external validation across countries, and interpretable outputs that officials can defend. The review lists precisely these as the priorities (Journal of Clinical Medicine).
FAQs#
Did AI fail to predict the loss of measles elimination status? That is not what the evidence shows. The forecasting study that found every model underestimated 2026 used classical statistical methods, not AI. A review of 46 studies also found no AI model in routine national measles surveillance, so AI was not the tool being relied upon. (Frontiers in Epidemiology)
What does "measles elimination" actually mean? It means endemic transmission has been interrupted: the same virus lineage has not circulated continuously for 12 months or more in a country. It does not mean there are no cases at all. (PAHO)
Which countries lost elimination status in November 2026? Bolivia, Mexico and the United States, following the Commission's meeting on 10 to 13 November. (PAHO)
Can machine learning predict where measles outbreaks will happen? It can rank areas by risk with useful accuracy in research settings. A US county study reported an AUC of 0.920 to 0.926 for XGBoost, and a Bangladesh district study reported 0.838. Both are retrospective, so they show promise rather than proven field impact. (JMIR Formative Research)
Are neural networks better than traditional epidemic models for measles? Sometimes, for specific tasks. One study found a neural network had lower forecast error than a mechanistic model across most windows, and combining the two improved results further. Those data were historical records from England and Wales. (PLOS Computational Biology)
How can the United States regain elimination status? By submitting a corrective action plan to PAHO and then showing it has been free of the virus for 12 months, according to news reporting of PAHO officials. PAHO's stated route is at least 95 per cent two-dose coverage in every community, with strong surveillance and response. (Reuters)
Does AI help design vaccines for preventable viral diseases? Researchers are applying it to antigen discovery, epitope prediction and immunogenicity assessment, but a recent review stresses data bias, under-representation of low- and middle-income populations and the need for interpretable models. Measles already has an effective vaccine. (Frontiers in Pharmacology)
References#
- Pan American Health Organization. PAHO urges countries to step up efforts to stop measles outbreaks and move towards elimination in the Americas. 17 November 2026. https://www.paho.org/en/news/17-11-2026-paho-urges-countries-step-efforts-stop-measles-outbreaks-and-move-towards
- Pan American Health Organization. Measles in the Americas: Questions and Answers, Technical Reference for Journalists and the Public. 17 November 2026. https://www.paho.org/en/news/17-11-2026-measles-americas-questions-and-answers-technical-reference-journalists-and-public
- Barbosa J. Remarks, media briefing on measles in the Americas. PAHO, 17 November 2026. https://www.paho.org/en/documents/remarks-bt-dr-jarbas-barbosa-media-briefing-measles-americas
- Centers for Disease Control and Prevention. Measles Cases and Outbreaks (updated 13 November 2026). https://www.cdc.gov/measles/data-research/index.html
- Importation-Driven Measles Resurgence and the Fragility of Elimination, Japan, 2024 to 2026. Emerging Infectious Diseases 2026;32(11). https://wwwnc.cdc.gov/eid/article/32/11/26-1187_article
- Ru B, Kujawski S, Afanador NL, et al. Predicting Measles Outbreaks in the United States: Evaluation of Machine Learning Approaches. JMIR Formative Research 2023;7:e42832. https://doi.org/10.2196/42832
- Shiddik MAB, Rahman MS. District-level measles outbreak prediction in Bangladesh using geospatial artificial intelligence. BMC Infectious Diseases 2026;26. https://doi.org/10.1186/s12879-026-14067-y
- Lau MSY, Becker A, Madden W, et al. Comparing and linking machine learning and semi-mechanistic models for the predictability of endemic measles dynamics. PLOS Computational Biology 2022;18(9):e1010251. https://doi.org/10.1371/journal.pcbi.1010251
- Madden WG, Jin W, Lopman B, et al. Deep neural networks for endemic measles dynamics: Comparative analysis and integration with mechanistic models. PLOS Computational Biology 2024. https://doi.org/10.1371/journal.pcbi.1012616
- Gondim A, Chukwu CW, Agusto FB. Insights on United States cumulative measles cases during the 2026 outbreak using ARIMA and generalized linear models. Frontiers in Epidemiology 2026. https://doi.org/10.3389/fepid.2026.1921780
- Baiasu AF, Rotaru-Zavaleanu A-D, Boldea A-M, et al. Bridging Traditional Modeling and Artificial Intelligence in Measles Epidemiology: Methods, Applications, and Future Directions, a Narrative Review. Journal of Clinical Medicine 2026;15. https://doi.org/10.3390/jcm15093242
- Branda F, Tomasso M, Ahmed MM, et al. Measles Tracker: a near-real-time data hub for measles surveillance. JAMIA Open 2025. https://doi.org/10.1093/jamiaopen/ooaf062
- Akingbola A, Adegbesan A, Adewole O, et al. Artificial intelligence for coordinating vaccine design, antiviral discovery, and real-world monitoring in the era of emerging and endemic viral threats. Frontiers in Pharmacology 2026. https://doi.org/10.3389/fphar.2026.1773609
- Reuters. US loses measles elimination status after nearly three decades. 17 November 2026 (news report, cited only for PAHO officials' description of the re-verification steps; no primary PAHO page on that step was retrieved). https://www.reuters.com/business/healthcare-pharmaceuticals/us-loses-measles-elimination-status-after-nearly-three-decades-2026-11-17/